Skip to content

DHA (Docosahexaenoic Acid) Deficiency

Smoked Salmon...Brain Food that's Good for the Eyes!
Salmon…Brain Food That’s Good for Your Eyes, Heart, Blood Vessels, Blood Sugar, Liver, Muscles, and Fights Inflammation!

What Is DHA?

Docosahexaenoic acid (DHA) is an essential omega-3 fatty acid that is abundant in the brain, being crucial in brain structure. As such DHA is a key component of neuronal membranes together with arachidonic acid (a major opposing omega-6 fatty acid), making up 15-20% of the brain’s dry mass.

This polyunsaturated fatty acid is obtained from fish sources of food.

In healthy human volunteers, positron emission tomography (PET) has shown that the normal human brain consumes 4.6 mg/day of DHA.1

DHA is particularly concentrated in highly active membranes such as nerve synapses (junctions) and photoreceptors in the eye (retina).

Q: How much DHA is in the retina?

A: DHA makes up more than 30% of the retina.2

In other roles, DHA is an  important building material for the eicosanoids, a large group of highly bioactive hormone-like substances including prostaglandins, leukotrienes, and thromboxanes that are involved in blood clotting, inflammation, and vasoconstriction.

DHA has been shown to increase insulin sensitivity as opposed to the opposite problem of insulin resistance, to improve muscle mass, and protect against non-alcoholic fatty liver disease.3

Egert et al. in a study of people aged 19 to 43 years with normal cholesterol showed that DHA intake significantly increased serum HDL (good) cholesterol. Also, DHA significantly decreased fasting serum triglycerides.4

What Is DHA Deficiency In Celiac Disease and/or Gluten Sensitivity?

Sources:
  1. Rapoport SI. Brain arachidonic and docosahexaenoic acid cascades are selectively altered by drugs, diet and disease. Prostaglandins Leukot Essent Fatty Acids. 2008 Sep-Nov;79(3-5):153-6. Epub 2008 Oct 29. []
  2. Richardson AJ. The importance of omega-3 fatty acids for behavior, cognition, and mood. Scandinavian Journal of Nutrition. 2003;47(2):92-8 []
  3. Espinosa A, Valenzuela R, González-Mañán D, D’Espessailles A, Guillermo Gormaz J, Barrera C, Tapia G. Prevention of liver steatosis through fish oil supplementation: correlation of oxidative stress with insulin resistance and liver fatty acid content. Arch Latinoam Nutr. 2013 Mar;63(1):29-36. []
  4. Egert S, Kannenberg F, Somoza V, et al. Dietary alpha-linolenic acid, EPA, and DHA have differential effects on LDL fatty acid composition but similar effects on serum lipid profiles in normolipidemic humans. J Nutr. 2009;139:861–868. doi: 10.3945/jn.108.103861 []

Dry Eyes, Chronic

Microscopic View of a Liver Granuloma. Courtesy pathology.med.umich.edu/greensonlab.

What Is Hepatic Granulomatous Disease?

H epatic granulomatous disease is an infiltrative chronic liver disorder characterized by growth of small granulomas.

Rather than being a final diagnosis, the presence of hepatic granulomas entails the need for further investigations towards identifying the underlying etiology, with a pathologist being at the center of the diagnostic process.1

Q: What are hepatic granulomas?

A: Hepatic granulomas are unique inflammatory formations that require liver biopsy for diagnosis.2

Hepatic granulomas develop through the interactions of T lymphocytes and macrophages, with the integral involvement of T-helper (T(H)) 1 or T(H)2 pathways or both, depending on the specific granulomatous disease.

Hepatic granulomas may be detected clinically by elevated levels of serum alkaline phosphatase and g-glutamyltransferase enzymes, damage to specific structures (e.g., intrahepatic bile ducts in primary biliary cirrhosis), or infrequently, progressive liver disease with portal hypertension and cirrhosis (e.g., sarcoidosis).

Systemic immunologic disorders, infectious diseases, drug hepatotoxicity, and reaction to neoplastic disease are the major causative factors responsible for granulomas in the liver.3

What Is Hepatic Granulomatous Disease In Celiac Disease and/or Gluten Sensitivity?

Sources:
  1. Turhan N, Kurt M, Ozderin YO, Kurt OK. Hepatic granulomas: a clinicopathologic analysis of 86 cases. Pathol Res Pract. 2011 Jun 15;207(6):359-65. doi: 10.1016/j.prp.2011.03.003. Epub 2011 Apr 30. []
  2. Bhardwaj SS, Saxena R, Kwo PY. Granulomatous liver disease. Curr Gastroenterol Rep. 2009 Feb;11(1):42-9. []
  3. Lagana SM1, Moreira RK, Lefkowitch JH. Hepatic granulomas: pathogenesis and differential diagnosis. Clin Liver Dis. 2010 Nov;14(4):605-17. doi: 10.1016/j.cld.2010.07.005. []

Subscriber Newsletter June 23, 2015

A Gluten Free Works Notification for Health Guide Subscribers Is this email not displaying correctly? View it in your browser. Subscriber Newsletter Dear << Test First Name >>:Welcome to the Gluten Free Works Health Guide Newsletter!… 

Cataracts

Glucose Meter Reading Showing Hypoglycemia. Courtesy Abbott.
Glucose Meter Reading.Courtesy Abbott.

What Is Diabetic Instability?

D iabetic instability, also called brittle diabetes, is poor control of blood sugar characterized by frequent rise (hyperglycemia) and fall (hypoglycemia). These fluctuations can be life-threatening and cause unnecessary complications.

Q: What are complications in diabetes?

A: Complications of diabetes include any/all of the following:

  • Peripheral neuropathy that causes burning, numbness, or tingling in the extremities.
  • Skin infections and ulcers that do not heal and can lead to amputation of toes, feet or legs.
  • Damage to retina that can progress to blindness.
  • Cataracts and glaucoma that impair vision and can cause blindness.
  • Increased susceptibility to serious infections of the genitourinary tract, lung and upper respiratory tract that can become systemic and life-threatening.
  • Kidney disease that can lead to kidney failure.
  • Heart disease that can lead to heart failure.
  • Vascular disease that can lead to stroke.
  • Impaired motility in digestive tract that can lead to dyspepsia and constipation.
  • Pregnancy complications.
  • Shortened life expectancy.

The main causes of brittleness include malabsorption, certain drugs (alcohol, antipsychotics), defective insulin absorption or degradation, defect of hyperglycemic hormones especially glucocorticoid and glucagon, and above all delayed gastric emptying as a result of autonomic neuropathy.1

What Is Diabetic Instability In Celiac Disease and/or Gluten Sensitivity?

Sources:
  1. Vantyghem MC, Press M. Management strategies for brittle diabetes. Ann Endocrinol (Paris). 2006 Sep;67(4):287-96. []

Bitot’s Spots 


Jaundice, or yellowing of the skin and sclera of eyes.
Jaundice, or yellowing of the skin and sclera of eyes, is a symptom of autoimmune hepatitis.

What Is Autoimmune Hepatitis?

A utoimmune hepatitis is an autoimmune attack against liver cells that is characterized by inflammation and results in chronic liver disease which includes low blood albumin and cirrhosis.

Autoimmune hepatitis is diagnosed by detection of autoantibodies in blood and liver biopsy.

Q: What is cirrhosis?

A: Cirrhosis is a degenerative process of the liver that can be fatal. Normal lobular liver structure is distorted and replaced with nodules of regenerating liver cells separated by bands of fibrous tissue that cannot properly carry out liver function and block the necessary flow of blood through the liver, ending in liver failure.

The liver is the largest organ within the body and lies mostly in the upper part of the abdomen on the right side just under the diaphragm. About 70% of liver tissue is made up of cube shaped cells called hepatocytes that do the main work of the liver. Other cells form structure and are arranged in single layers around blood vessels, sinusoids, and bile ducts.

Bile ducts carry bile, a greenish brown liquid made by the liver, to the gall bladder for storage until needed to aid in the digestion and absorption of fat from the small intestine. Bile emulsifies fat eaten in the diet so that the pancreatic enzyme called lipase can break it down into its fatty acid and glycerol components.

The liver is a very busy organ, carrying out over 500 metabolic processes! Nutritionally, it is the first to receive all the blood carrying nutrients freshly absorbed from the digestive tract. Hepatocytes then convert the nutrients to provide the body with energy, a host of amino acids as building blocks for numerous cell activities, and proteins such as albumin and fibrinogen. In fact, hepatocytes build the structural proteins for the liver itself. Imagine the array of nutrients the liver uses and keeps at its disposal for its metabolic functions. Included in liver storage are vital vitamins and minerals such as vitamin A and vitamin B12.

As a detoxifier, Kupffer cells located in the sinusoids act like amoebas to engulf and digest unwanted matter. As a blood cleanser, the liver removes waste products produced by normal metabolism and toxic substances and rids it by preparing these substances for elimination in urine, such as ammonia converted to urea, and/or excreting them in bile for eventual elimination in stool. Bile is continually made by the liver from phospholipids salt, cholesterol, aging blood cells it removes from circulation.

Autoimmune hepatitis is classified into several types. Type 1 autoimmune hepatitis is the most common form in North America. Type 1 can occur at any age; however, it most often starts in adolescence or young adulthood. People with type 1 autoimmune hepatitis commonly have other autoimmune disorders (see listed below).

Type 2 autoimmune hepatitis is less common and occurs more often in children than adults. People with type 2 can also have any of the autoimmune disorders (see listed below).

Both types of autoimmune hepatitis are treated with prednisone, a corticosteroid hormone to control inflammation and reduce the body’s immune activity against the liver.1

What Is Autoimmune Hepatitis In Celiac Disease and/or Gluten Sensitivity?

Sources:
  1. National Digestive Diseases Information Clearinghouse []

Uveitis, Non-Infectious  

Courtesy Wikipedia.com
Parathyroid Glands in the Neck. Courtesy Wikipedia.com

What Is Secondary Hyperparathyroidism?

S econdary hyperparathyroidism is a parathyroid disorder resulting from hypocalcemia (low blood calcium level) that is characterized by excessive production of parathyroid hormone in the attempt to normalize the low blood calcium by releasing calcium from bone.

Parathyroid hormone is produced by the four pea sized parathyroid glands that are located on the thyroid gland in the front of the neck. In part, because the thyroid and parathyroid glands share the same anatomic place in the body and because they have similar names, they are often confused although they have completely different actions.

Parathyroid hormone regulates calcium and the opposing mineral phosphorus in the blood. In secondary hyperparathyroidism, calcium blood levels are low to normal while phosphorus levels are increased which stimulates the outpouring of parathyroid hormone.

Q: How does secondary hyperparathyroidism differ from primary hyperparathyroidism?

A: In primary hyperparathyroidism blood calcium is high and phosphorus is low, which is the opposite of secondary hyperparathyroidism.

The most common cause of secondary hyperparathyroidism is kidney disease causing failure to reabsorb calcium followed by vitamin D deficiency and malabsorption.

What Is Secondary Hyperparathyroidism In Celiac Disease and/or Gluten Sensitivity?

Xerophthalmia

Parathyroid gland anatomyWhat Is Idiopathic Hypoparathyroidism?

I diopathic hypoparathyroidism is a metabolic condition that results from reduced secretion or impaired action of parathyroid hormone (PTH) which results in a combination of low calcium and elevated phosphorus levels in the body.

Calcium and phosphorus are minerals that act in opposition to each other in the body. Idiopathic means the cause is not known.

Parathyroid hormone is produced by the four pea sized parathyroid glands that are located on the thyroid gland in the front of the neck. Partly because the thyroid and parathyroid glands share the same anatomic place in the body and partly because they have similar names, they are often confused although they have completely different actions.

Q: What does parathyroid hormone do in the body?

A: This vital hormone maintains a correct balance of calcium and phosphorous in the bloodstream and ultimately has an effect on all organs because of the complexity of intracellular calcium physiology.1 

Parathyroid hormone is required to sustain life, therefore undetected or misdiagnosed hypoparathyroidism may pose a significant threat to health outcomes, as its presence may increase disease and mortality in affected individuals.

The clinical consequences of parathyroid hormone deficiency or impaired receptor action involve many body functions. In some patients, however, its manifestation may be non-specific, and in these cases the correct diagnosis may be easily missed.

Digestive manifestations of hypoparathyroidism are few and consist mainly of steatorrhea due to insufficient meal-stimulated cholecystokinin secretion by the duodenal mucosa.2

Laboratory measurements show hypocalcemia (low blood calcium level), hyperphosphatemia (high blood phosphate level), and inappropriately low or undetectable parathyroid hormone levels. Treatment consists of oral calcium supplementation and vitamin D derivatives.3

Idiopathic hypoparathyroidism is rare, although there is a growing incidence of the autoimmune form of hypoparathyroidism, which may occur in combination with other autoimmune diseases such as celiac disease.

What Is Idiopathic Hypoparathyroidism In Celiac Disease and/or Gluten Sensitivity?

Sources:
  1. Abboud B, Daher R, Boujaoude J. Digestive manifestations of parathyroid disorders. World J Gastroenterol. 2011 Sep 28;17(36):4063-6. doi: 10.3748/wjg.v17.i36.4063. []
  2. Abboud B, Daher R, Boujaoude J. Digestive manifestations of parathyroid disorders. World J Gastroenterol. 2011 Sep 28;17(36):4063-6. doi: 10.3748/wjg.v17.i36.4063. []
  3. Krysiak R, Handzlik-Orlik G, Kedzia A, Machnik G, Okopień B. Hypoparathyroidism: the present state of art. Wiad Lek. 2013;66(1):18-29. []

Blepharitis, Non-Infectious (Swollen Eyelids)

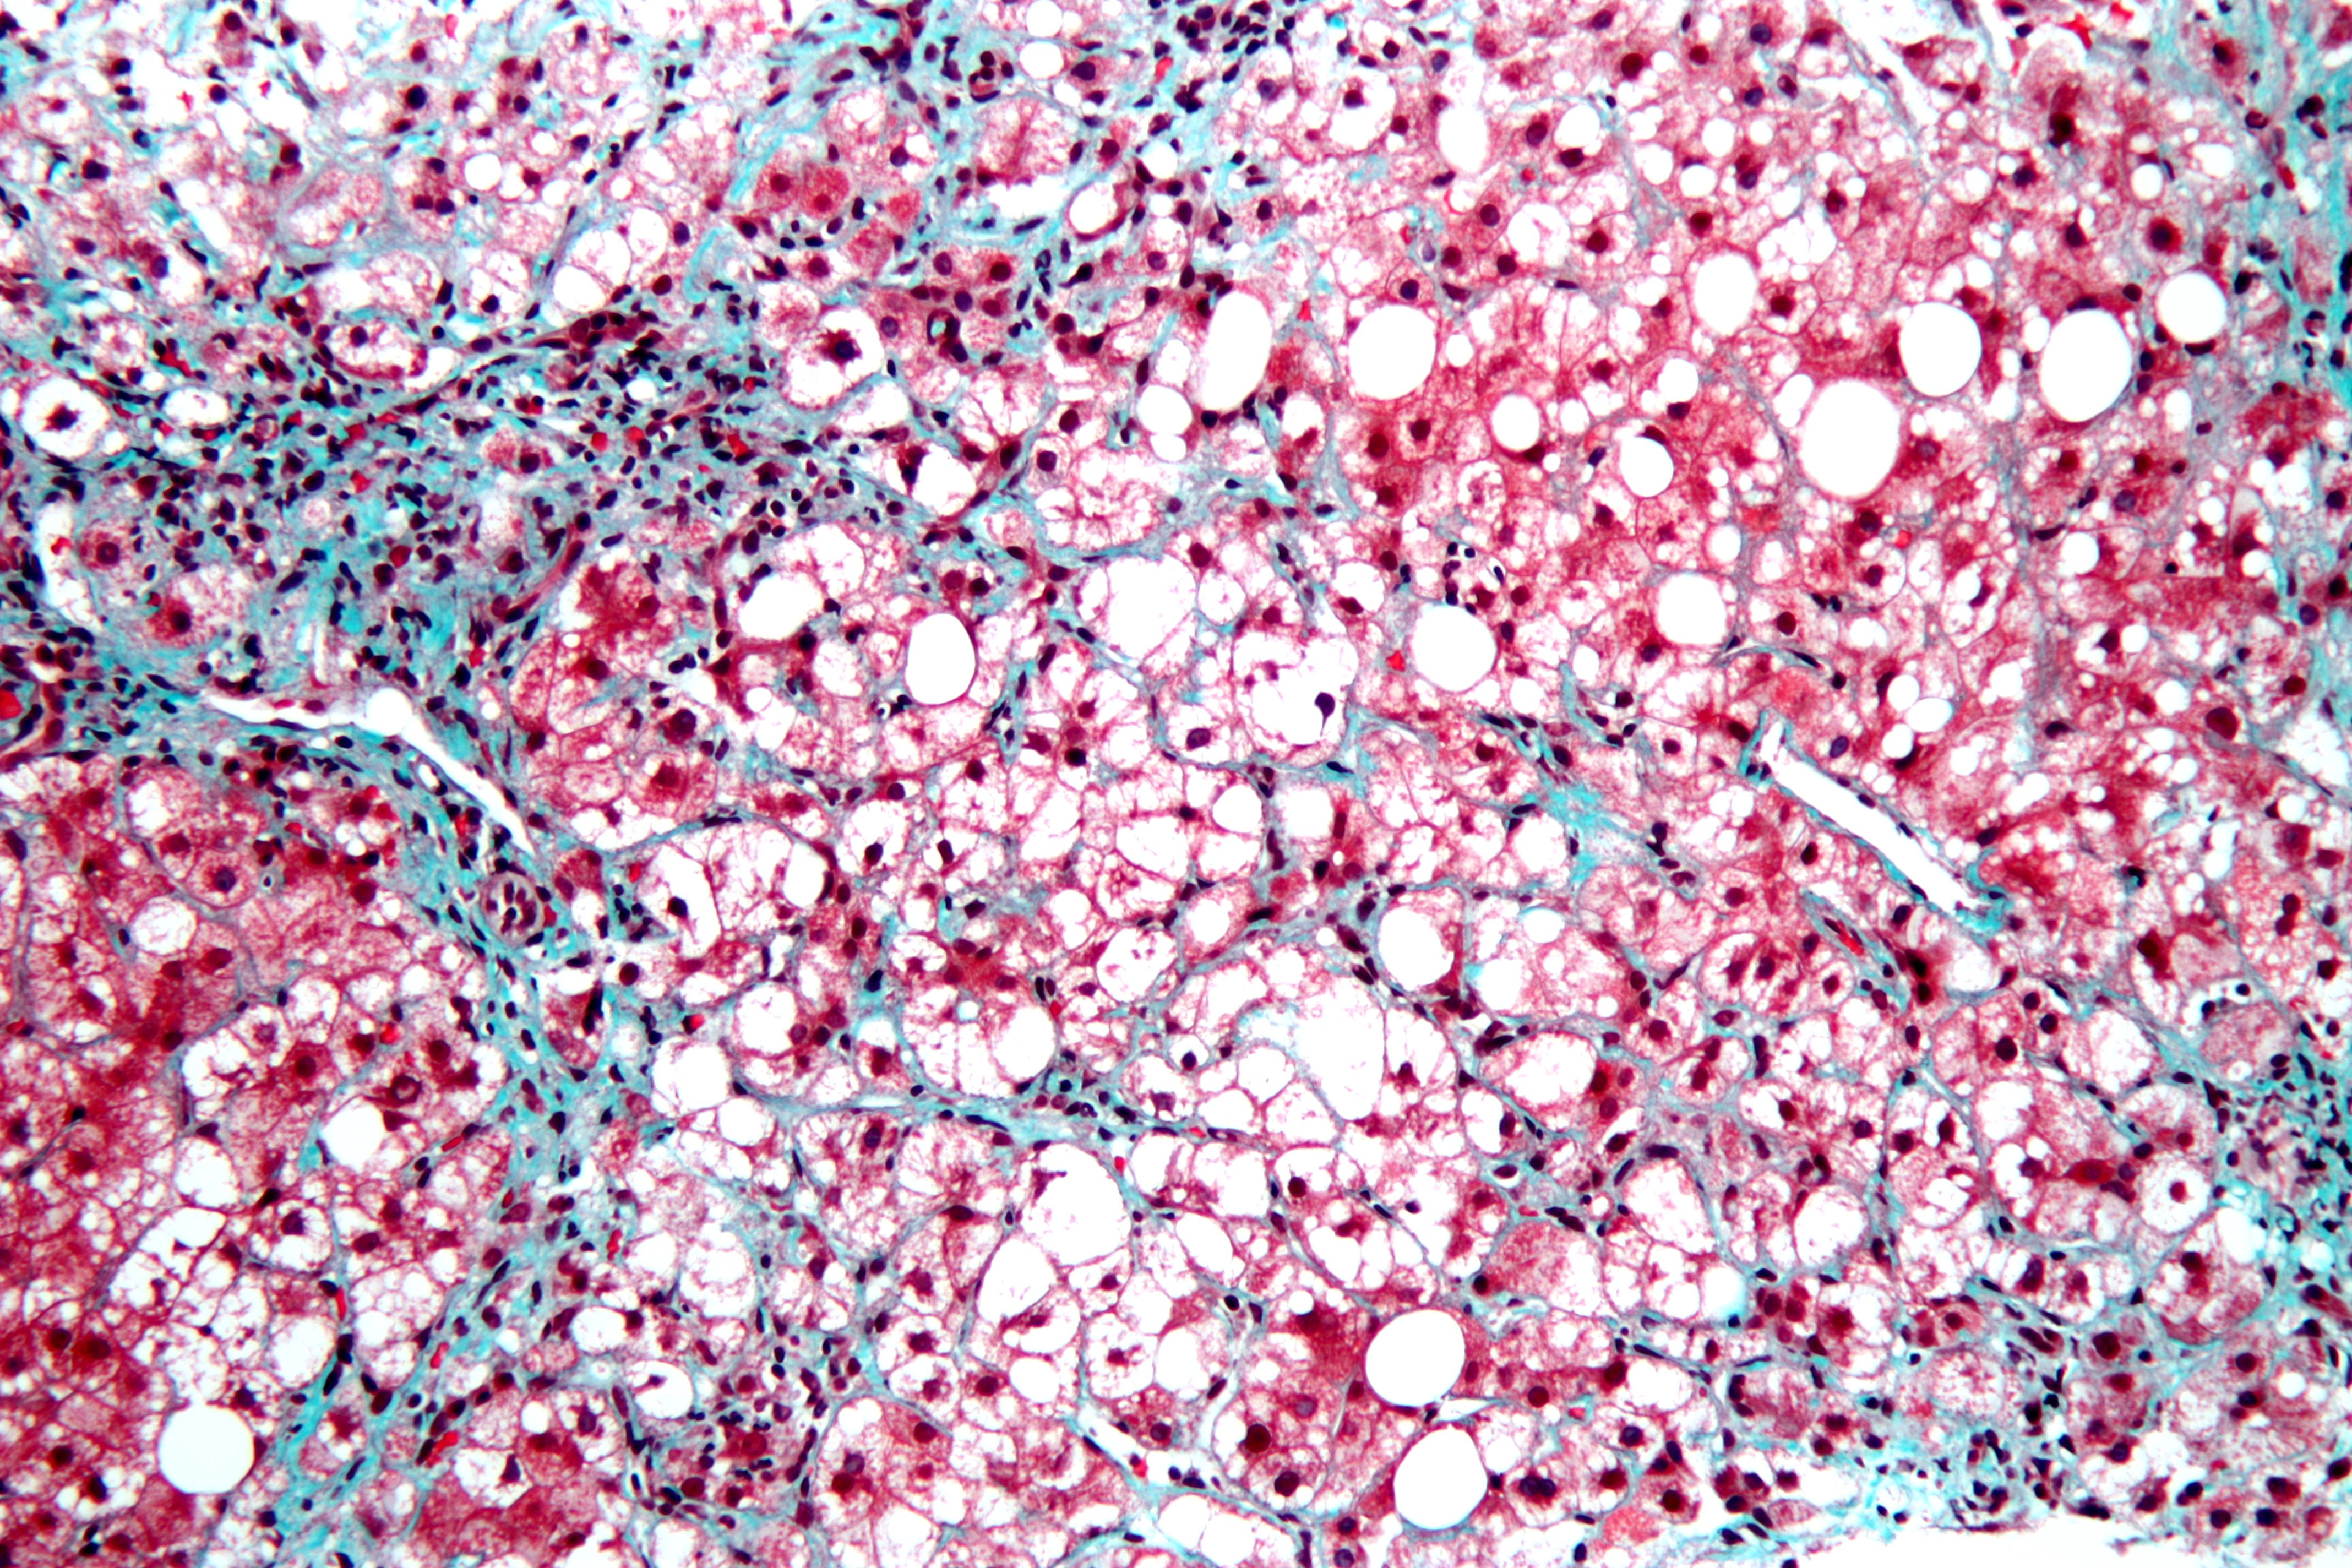
This is a stained liver biopsy sample showing advanced cellular changes in non-alcoholic fatty liver disease. Blue is fibrosis. White is fat accumulation in degenerated cells. Courtesy of Nephron's work.
This is a stained liver biopsy sample showing advanced cellular changes in non-alcoholic fatty liver disease. Blue is fibrosis. White is fat accumulation in degenerated cells. Courtesy of Nephron’s work.

What Is Non-Alcoholic Fatty Liver Disease?

N on-alcoholic fatty liver is a non-inflammatory liver disorder characterized by degenerative changes in the liver caused by excessive accumulation of lipid (fat) in hepatocytes (liver cells) that is called free fatty acid-generated lipotoxicity.

Non-alcoholic fatty liver shows an increase in liver enzymes called transaminases.

Q: What are the enzymes that increase?

A: The transaminases that increase are ALT and AST. ALT is the abbreviation for alanine aminotransferase enzyme and AST is the abbreviation for aspartate aminotransferase enzyme. They are commonly measured in blood tests to determine liver function and when elevated indicate inflammation.

What Is Non-Alcoholic Fatty Liver In Celiac Disease and/or Gluten Sensitivity?

Dry Eye, Autoimmune (Keratoconjunctivitis Sicca)

gastrointestinal complications in diabetes symptom in gluten and celiac diseaseWhat Are Gastro-Intestinal Complications Of Type 1 Diabetes?

G astrointestinal complications of type I diabetes mellitus are functional or organic changes that result from diabetes affecting every organ of the gastrointestinal tract.

Q: How do gastrointestinal tract complications affect diabetes?

A: Impaired function of individual digestive organs in diabetes can significantly influence level of diabetes compensation and vice versa. On the other side, unsatisfactory diabetes compensation can result in manifestation of digestive problems.

The most frequent (55 to 75%) and the most serious clinical complication is diabetic gastroparesis characterized by impaired evacuation and motility of the stomach and small intestine. Gastroparesis results in nausea, vomiting, early fullness after eating and constipation.

Treatment is with prokinetics. These oral medicines help motility and transport of food in the esophagus, stomach and intestines and improve sphincter function to keep food from going backwards.

Gastroesophageal reflux and heartburn are other complications in diabetes. These are treated with antacids and acid reducing medications.

Various autoimmune disease interfere with digestion. One connection between diabetes mellitus and the gastrointestinal tract can be celiac disease.1

What Are Gastro-Intestinal Complications Of Diabetes In Celiac Disease and/or Gluten Sensitivity?

Sources:
  1. Perusicova J. Gastrointestinal complications in diabetes mellitus. Vnitri Lekarstvi. May 2004;50(5):338-43. []

Keratomalacia

Image From Gray's Anatomy. Courtesy Wikipedia.org
Image  of Pancreas From Gray’s Anatomy. Courtesy Wikipedia.org

What Is Pancreatic Insufficiency?

P ancreatic insufficiency is a disorder characterized by insufficient exocrine production of pancreatic enzymes for normal digestion of fats, proteins, and carbohydrates that results in maldigestion of these foodstuffs.

Pancreatic insufficiency also causes malabsorption of the fat-soluble vitamins: vitamin A, vitamin D, vitamin E, and vitamin K.

Q: What are the exocrine enzymes produced by the pancreas?

A: Exocrine enzymes produced by the pancreas include amylase for the digestion of carbohydrates, lipase for the digestion of fats, and protease for the digestion of proteins.

While lipases and amylase are secreted in the active form, proteases are secreted as pro-enzymes (need to be activated). Trypsinogen is converted to its active form trypsin in the duodenum by enterokinase, a protease secreted by the enterocytes (surface cells that line the duodenum), and trypsin in turn activates the other pancreatic proteases.1

Pancreatic enzymes are released by the pancreas into the internal pancreatic duct that empties into the common bile duct from which they are pumped through the Sphincter of Odi directly into the duodenum as needed. Tthe Sphincter of Odi is a strong circular muscle that controls the entrance of pancreatic enzymes into the duodenum.

After a meal, enzyme secretion into the duodenum increases quickly reaching peak output within the first 20 to 60 minutes, then decreasing to a stable level before reaching an interdigestive level at the end of the digestive period, that is, about 4 hours after meal intake.2

Medical treatment is with medication that contains enzymes to break down carbohydrates, fats, and protein in food at mealtime. This treatment is safe, effective, and has few side effects.

What Is Pancreatic Insufficiency In Celiac Disease and/or Gluten Sensitivity?

Sources:
  1. Fieker A, Philpott J, Armand M. Enzyme replacement therapy for pancreatic insufficiency: present and future. Clin Exp Gastroenterol. 2011;4:55-73. doi: 10.2147/CEG.S17634. []
  2. Fieker A, Philpott J, Armand M. Enzyme replacement therapy for pancreatic insufficiency: present and future. Clin Exp Gastroenterol. 2011;4:55-73. doi: 10.2147/CEG.S17634. []